Aucun résultat ne correspond à votre mot-clé.
Contenu

Vous vous êtes déconnecté avec succès.


Pas encore enregistré ?
Applications chirurgicales et ambulatoires
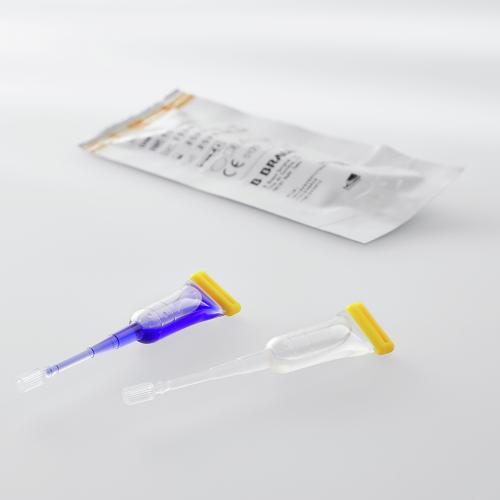
Découvrez les avantages des différents types de colles tissulaires Histoacryl® pour les applications chirurgicales et ambulatoires.


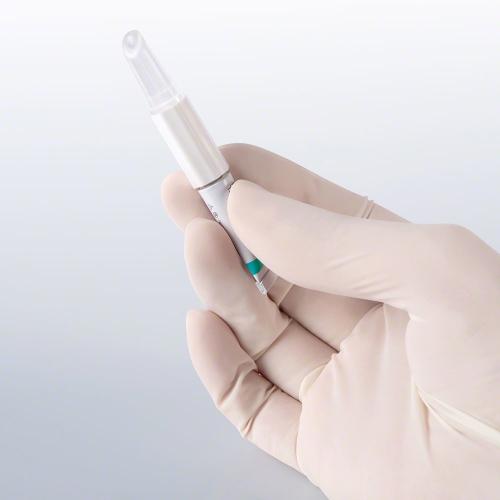
Histoacryl® LapFix permet une fixation atraumatique des mailles. Elle est mieux tolérée par les patients que les méthodes de fixation traditionnelles. Elle réduit le risque de douleur chronique postopératoire par rapport aux méthodes de fixation traditionnelles11-12.
Colle tissulaire pour refermer les incisions chirurgicales et les coupures simples induites par un traumatisme et qui ont été soigneusement nettoyées. Histoacryl® Flexible est bien adaptée à la fermeture des plaies chroniques qui nécessitent plus de flexibilité et un soutien solide. Histoacryl® Octyl est une version liquide stérile facile à appliquer grâce à une viscosité accrue et une polymérisation rapide en 30 secondes1-3.
Colle tissulaire pour la fixation atraumatique des mailles, indiquée principalement pour la chirurgie de la hernie inguinale. Application facile avec Histoacryl® LapFix11-16.
La colle tissulaire convient à la sclérothérapie des veines dilatées de l'œsophage et des veines sous-muqueuses de la couche muqueuse de la paroi de l'estomac4-10. La sclérothérapie consiste à injecter un liquide dans le vaisseau sanguin pour le fermer.
Le Professeur Cárdenas offre des perspectives et une expertise précieuses dans ce domaine et fournit un aperçu complet de la préparation et de l'application de cette technique.
Dans cette vidéo, le Professeur Cárdenas montre comment le traitement avec Histoacryl® a été réalisé avec succès chez un patient souffrant de varices gastriques.
Onepager assortiment Histoacryl®
Colles tissulaires pour les applications chirurgicales et ambulatoires
pdf, 860.3 KB
Onepager Histoacryl® information pour le patient
Tout ce que vous devez savoir après un traitement avec la colle cutanée Histoacryl®
pdf, 1.6 MB
Certificat Histoacryl® superhéro
Page à colorier
pdf, 160.2 KB
Certificat Histoacryl® superhéroïne
Page à colorier
pdf, 163.6 KB
Références
Skin closure
1. Elmasalme FN, Matbouli SA, Zuberi MS. Use of tissue adhesive in the closure of small incisions and lacerations. J Pediatr Surg. (1995) 30:6 (837-8).
Surgical wounds
2. Dumville JC, Coulthard P, Worthington HV, Riley P, Patel N, Darcey J, Esposito M, van der Elst M, van Waes OJ. Tissue adhesives for closure of surgical incisions. Cochrane Database Syst Rev. (2014) Nov 28;(11)
3. Yulevich A, Cohen Z, Mares AJ. Use of N-Butyl-2-Cyanoacrylate (Histoacryl®) in Closure of Thoracoscopic an Laparoscopic Surgical Wounds in Children. Pediatric Endosurg. (1998) 2:1 (31-4).
Sclerotherapy
4. Feretis C, Dimopoulos C, Benakis P, Kalliakmanis B, Apostolidis N. N-butyl-2-cyanoacrylate (Histoacryl) plus sclerotherapy versus sclerotherapy alone in the treatment of bleeding esophageal varices: a randomized prospective study. Endoscopy. (1995) 27:5 (355-7).
5. Kozieł S, Kobryń K, Paluszkiewicz R, Krawczyk M, Wróblewski T. Endoscopic treatment of gastric varices bleeding with the use of n-butyl-2 cyanoacrylate. Prz Gastroenterol (2015) 10:4 (239–243).
6. Jang WS, Shin HP, Lee JI, Joo KR, Cha JM, Jeon JW, Lim JU. Proton pump inhibitor administration delays rebleeding after endoscopic gastric variceal obturation. World journal of Gastroenterology (2014) 20:45 (17127-17131).
7. Prachayakul V, Aswakul P, Chantarojanasiri T, Leelakusolvong S. Factors influencing clinical outcomes of Histoacrylglue injection-treated gastric variceal hemorrhage. World J Gastroenterol. (2013) 19:15 (2379–2387).
8. Lo GH, Lin CW, Perng DS, Chang CY, Lee CT, Hsu CY, Wang HM, Lin HC. A retrospective comparative study of histoacryl injection and banding ligation in the treatment of acute type 1 gastric variceal hemorrhage. Scand J Gastroenterol. (2013) 48:10 (1198-204).
9. Feretis C, Dimopoulos C, Benakis P, Kalliakmanis B, Apostolidis N. N-butyl-2-cyanoacrylate (Histoacryl) plus sclerotherapy versus sclerotherapy alone in the treatment of bleeding esophageal varices: a randomized prospective study. Endoscopy. (1995) 27:5 (355-7).
10. Tan PC, Hou MC, Lin HC, Liu TT, Lee FY, Chang FY, Lee SD. A randomized trial of endoscopic treatment of acute gastric variceal hemorrhage: N-butyl-2-cyanoacrylate injection versus band ligation. Hepatology. (2006) 43:4 (690-7).
Mesh fixation
11. Hoyuela C, Juvany M, Carvajal F, Veres A, Troyano D, Trias M, Martrat A, Ardid J, Obiols J, López-Cano M. Randomized clinical trial of mesh fixation with glue or sutures for Lichtenstein hernia repair. Br J Surg. (2017) 104:6 (688-694).
12. Hoyuela C, Juvany M, Carvajal F, Veres A, Troyano D, Trias M, Martrat A, Ardid J, Obiols J, López-Cano M. Randomized clinical trial of mesh fixation with glue or sutures for Lichtenstein hernia repair. Br J Surg. (2017) 104:6 (688-694).
13. Helbling C, Schlumpf R. Sutureless Lichtenstein: first results of a prospective randomized clinical trial. Hernia. (2003) 7:2 (80-4).
14. Kim-Fuchs C, Angst E, Vorburger S, Helbling C, Candinas D, Schlumpf R. Prospective randomized trial comparing sutured with sutureless mesh fixation for Lichtenstein hernia repair: long-term results. Hernia. (2012) 16:1 (21-7).
15. Testini M, Lissidini G, Poli E, Gurrado A, Lardo D, Piccinni G. A singlesurgeon randomized trial comparing sutures, N-butyl-2-cyanoacrylate and human fibrin glue for mesh fixation during primary inguinal hernia repair. Can J Surg. (2010) 53:3 (155-60
16. Kukleta JF, Freytag C, Weber M. Efficiency and safety of mesh fixation in laparoscopic inguinal hernia repair using n-butyl cyanoacrylate: long-term biocompatibility in over 1,300 mesh fixations. Hernia. (2012) 16:2 (153–62).