Er zijn geen resultaten gevonden voor jouw zoekopdracht.
Inhoud

U bent succesvol uitgelogd.

Nog niet geregistreerd?
Chirurgische en poliklinische toepassingen
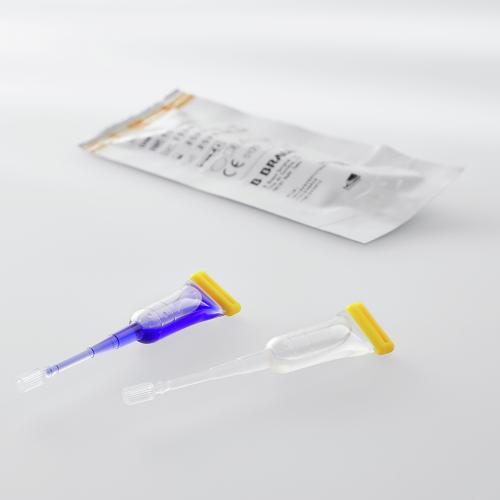
Ontdek de voordelen en veelzijdige toepassingen van de verschillende soorten Histoacryl® weefsellijm.


Chirurgische meshfixatie
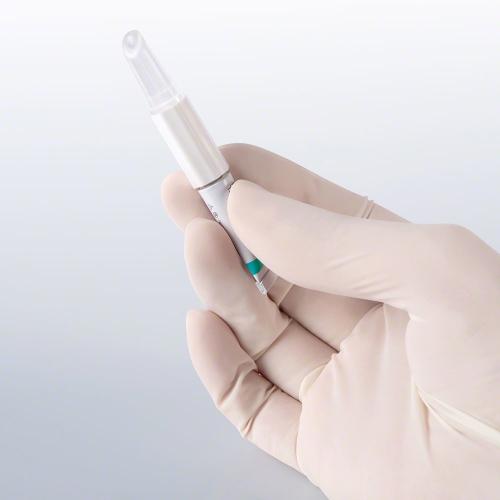
Histoacryl® LapFix zorgt voor een atraumatische fixatie van meshes. Er is vastgesteld dat deze beter wordt verdragen door patiënten dan traditionele fixatiemethoden. Het vermindert het risico op postoperatieve chronische pijn in vergelijking met traditionele fixatiemethoden11-12.
Ontdek Histoacryl® LapFixWeefsellijm voor het sluiten van chirurgische incisies en eenvoudige door trauma veroorzaakte snijwonden die grondig zijn gereinigd. Histoacryl® Flexible is zeer geschikt voor het sluiten van chronische wonden die om meer flexibiliteit vragen en krachtige wondondersteuning nodig hebben. Histoacryl® Octyl is een steriele vloeibare variant die gemakkelijk is aan te brengen door verhoogde viscositeit en snelle polymerisatie in 30 seconde1-3.
Weefsellijm voor atraumatische meshfixatie, voornamelijk bij liesbreukchirurgie. Gemakkelijke applicatie met Histoacryl® LapFix11-16.
Weefsellijm geschikt voor sclerotherapie van verwijde aderen in de slokdarm en submucosale aders in de slijmvlieslaag van de maagwand4-10. Sclerotherapie is het inspuiten van een vloeistof in het bloedvat waardoor dit dichtgaat.
Prof. Cárdenas biedt waardevolle inzichten en expertise op dit gebied en geeft een uitgebreid overzicht van de voorbereiding en toepassing van deze techniek.
In deze video laat Prof. Cárdenas zien hoe de behandeling met Histoacryl® succesvol is uitgevoerd bij een patiënt met maagvarices.
Onepager Histoacryl® assortiment
Weefsellijm voor chirurgische en poliklinische toepassingen
pdf, 856.2 KB
Onepager Histoacryl® patiënteninformatie
Alles wat je wil weten na behandeling met Histoacryl® huidlijm
pdf, 1.6 MB
Certificaat Histoacryl® superheld jongen
Kleurplaat
pdf, 548.8 KB
Certificaat Histoacryl® superheld meisje
Kleurplaat
pdf, 552.1 KB
Referenties
Skin closure
1. Elmasalme FN, Matbouli SA, Zuberi MS. Use of tissue adhesive in the closure of small incisions and lacerations. J Pediatr Surg. (1995) 30:6 (837-8).
Surgical wounds
2. Dumville JC, Coulthard P, Worthington HV, Riley P, Patel N, Darcey J, Esposito M, van der Elst M, van Waes OJ. Tissue adhesives for closure of surgical incisions. Cochrane Database Syst Rev. (2014) Nov 28;(11)
3. Yulevich A, Cohen Z, Mares AJ. Use of N-Butyl-2-Cyanoacrylate (Histoacryl®) in Closure of Thoracoscopic an Laparoscopic Surgical Wounds in Children. Pediatric Endosurg. (1998) 2:1 (31-4).
Sclerotherapy
4. Feretis C, Dimopoulos C, Benakis P, Kalliakmanis B, Apostolidis N. N-butyl-2-cyanoacrylate (Histoacryl) plus sclerotherapy versus sclerotherapy alone in the treatment of bleeding esophageal varices: a randomized prospective study. Endoscopy. (1995) 27:5 (355-7).
5. Kozieł S, Kobryń K, Paluszkiewicz R, Krawczyk M, Wróblewski T. Endoscopic treatment of gastric varices bleeding with the use of n-butyl-2 cyanoacrylate. Prz Gastroenterol (2015) 10:4 (239–243).
6. Jang WS, Shin HP, Lee JI, Joo KR, Cha JM, Jeon JW, Lim JU. Proton pump inhibitor administration delays rebleeding after endoscopic gastric variceal obturation. World journal of Gastroenterology (2014) 20:45 (17127-17131).
7. Prachayakul V, Aswakul P, Chantarojanasiri T, Leelakusolvong S. Factors influencing clinical outcomes of Histoacrylglue injection-treated gastric variceal hemorrhage. World J Gastroenterol. (2013) 19:15 (2379–2387).
8. Lo GH, Lin CW, Perng DS, Chang CY, Lee CT, Hsu CY, Wang HM, Lin HC. A retrospective comparative study of histoacryl injection and banding ligation in the treatment of acute type 1 gastric variceal hemorrhage. Scand J Gastroenterol. (2013) 48:10 (1198-204).
9. Feretis C, Dimopoulos C, Benakis P, Kalliakmanis B, Apostolidis N. N-butyl-2-cyanoacrylate (Histoacryl) plus sclerotherapy versus sclerotherapy alone in the treatment of bleeding esophageal varices: a randomized prospective study. Endoscopy. (1995) 27:5 (355-7).
10. Tan PC, Hou MC, Lin HC, Liu TT, Lee FY, Chang FY, Lee SD. A randomized trial of endoscopic treatment of acute gastric variceal hemorrhage: N-butyl-2-cyanoacrylate injection versus band ligation. Hepatology. (2006) 43:4 (690-7).
Mesh fixation
11. Hoyuela C, Juvany M, Carvajal F, Veres A, Troyano D, Trias M, Martrat A, Ardid J, Obiols J, López-Cano M. Randomized clinical trial of mesh fixation with glue or sutures for Lichtenstein hernia repair. Br J Surg. (2017) 104:6 (688-694).
12. Hoyuela C, Juvany M, Carvajal F, Veres A, Troyano D, Trias M, Martrat A, Ardid J, Obiols J, López-Cano M. Randomized clinical trial of mesh fixation with glue or sutures for Lichtenstein hernia repair. Br J Surg. (2017) 104:6 (688-694).
13. Helbling C, Schlumpf R. Sutureless Lichtenstein: first results of a prospective randomized clinical trial. Hernia. (2003) 7:2 (80-4).
14. Kim-Fuchs C, Angst E, Vorburger S, Helbling C, Candinas D, Schlumpf R. Prospective randomized trial comparing sutured with sutureless mesh fixation for Lichtenstein hernia repair: long-term results. Hernia. (2012) 16:1 (21-7).
15. Testini M, Lissidini G, Poli E, Gurrado A, Lardo D, Piccinni G. A singlesurgeon randomized trial comparing sutures, N-butyl-2-cyanoacrylate and human fibrin glue for mesh fixation during primary inguinal hernia repair. Can J Surg. (2010) 53:3 (155-60
16. Kukleta JF, Freytag C, Weber M. Efficiency and safety of mesh fixation in laparoscopic inguinal hernia repair using n-butyl cyanoacrylate: long-term biocompatibility in over 1,300 mesh fixations. Hernia. (2012) 16:2 (153–62).